
When you think of hospitals, you think of hallways. Here’s why we desi
In 2008, Rwanda was freshly tilled soil. Streets have been swept, lawns ended up manicured, and training and wellness treatment have been certain. The genocide of 1994 experienced stripped a folks of dignity and wrecked a era of life the nation had found the depths to which humanity could fall. But 14 yrs afterwards, just after targeted investments in wellness, schooling, housing, financial reconstruction, and reconciliation, Rwanda was abundant and hopeful. It was shedding histories of colonialism and ethnic division and recalibrating its upcoming toward shared financial and social progress.
To aid in strengthening the country’s overall health care procedure, Dr. Paul Farmer and his organization Partners In Wellbeing had been requested by the Rwandan federal government to check with. A critical factor of this collaboration would be a new goal-crafted medical center in the distant northern hamlet of Butaro.
At that time, I was studying architecture. Soon after hearing Farmer lecture, I questioned him which architects he was working with and how I might be of provider. He explained to me that few experienced ever reached out to him, and his business was typically still left to structure and establish by itself, with just the sources it currently experienced. He described the failure of Western “experts” as a remnant of colonial energy. Outside designers performing on projects for the underserved, he stated, were being intoxicated by fashionable unexpected emergency clinics in transport containers. They hardly ever stopped to inquire if persons preferred to acquire health treatment in an industrial waste item.
He also explained the dystopia produced by fashionable engineering, with its ostensibly low-cost, simply deployable clinical treatment, panacea solutions to consuming drinking water, and procedural hacks. He named this gear “junk for the poor” and explained it filling storage closets, sitting damaged in hallways, or lingering, inoperable, in healthcare clinics the entire world in excess of.
Farmer’s direct engineer in Rwanda, Bruce Nizeye, desired enable developing the medical center in Butaro, and he invited me to join him there in 2008. I jumped at the possibility. Most of the clinics and hospitals Partners In Overall health experienced earlier constructed ended up additions or renovations to hospitals. The Butaro healthcare facility was, at the time, the largest venture it had ever intended and created from the ground up. The shopper was the governing administration of Rwanda, and the medical center desired to tackle the epidemic of tuberculosis that was ravaging lousy communities all-around the globe.
Dr. Michael Abundant, an expert on tuberculosis and its multidrug-resistant variants, was then the director of Associates In Health’s Rwanda operations (via its sister group Inshuti Mu Buzima) and an architecture junkie. Medical center hallways, he described, were being the significant challenge in the transmission of multidrug-resistant tuberculosis. Patients waiting around in these spaces with out home windows or airflow would cough on every other, become coinfected with drug-resistant variants, and then carry them back again to their communities. In the hallways of hospitals, buildings intended to recover, the epidemic had begun.
“We have been seeking to style hallways out of hospitals for many years,” Prosperous told me. Naïvely, I requested, “Shouldn’t a modern hospital use a mechanical procedure to ventilate its areas?” Like a individual instructor, he explained that mechanical techniques hardly ever work as developed. And in some cases, he mentioned, they are far too pricey to preserve. When they break or are turned off for budgetary good reasons, the spaces have even worse airflow than people with basic home windows or out of doors waiting locations. Far better mechanical techniques do not meet up with people wherever they are.
Dr. Edward Nardell, a further tuberculosis expert at Associates In Health and fitness, pointed me to a analyze in Peru that showed how older, colonial-period hospitals, designed with generous home windows, tall ceilings, and open-air waiting places, were far better ready to protect against the transmission of tuberculosis than more recent kinds built to continue to keep mechanically conditioned air from leaking out. Nardell also released me to Florence Nightingale’s Notes on Hospitals and her spatial approaches to improve airflow and decrease disease transmission. I realized that there ended up common ideas of building functionality that transcend tradition, context, and time. We sought to identify more of these truths and insert them into the structure of the Butaro hospital.

The Suitable to Breathe
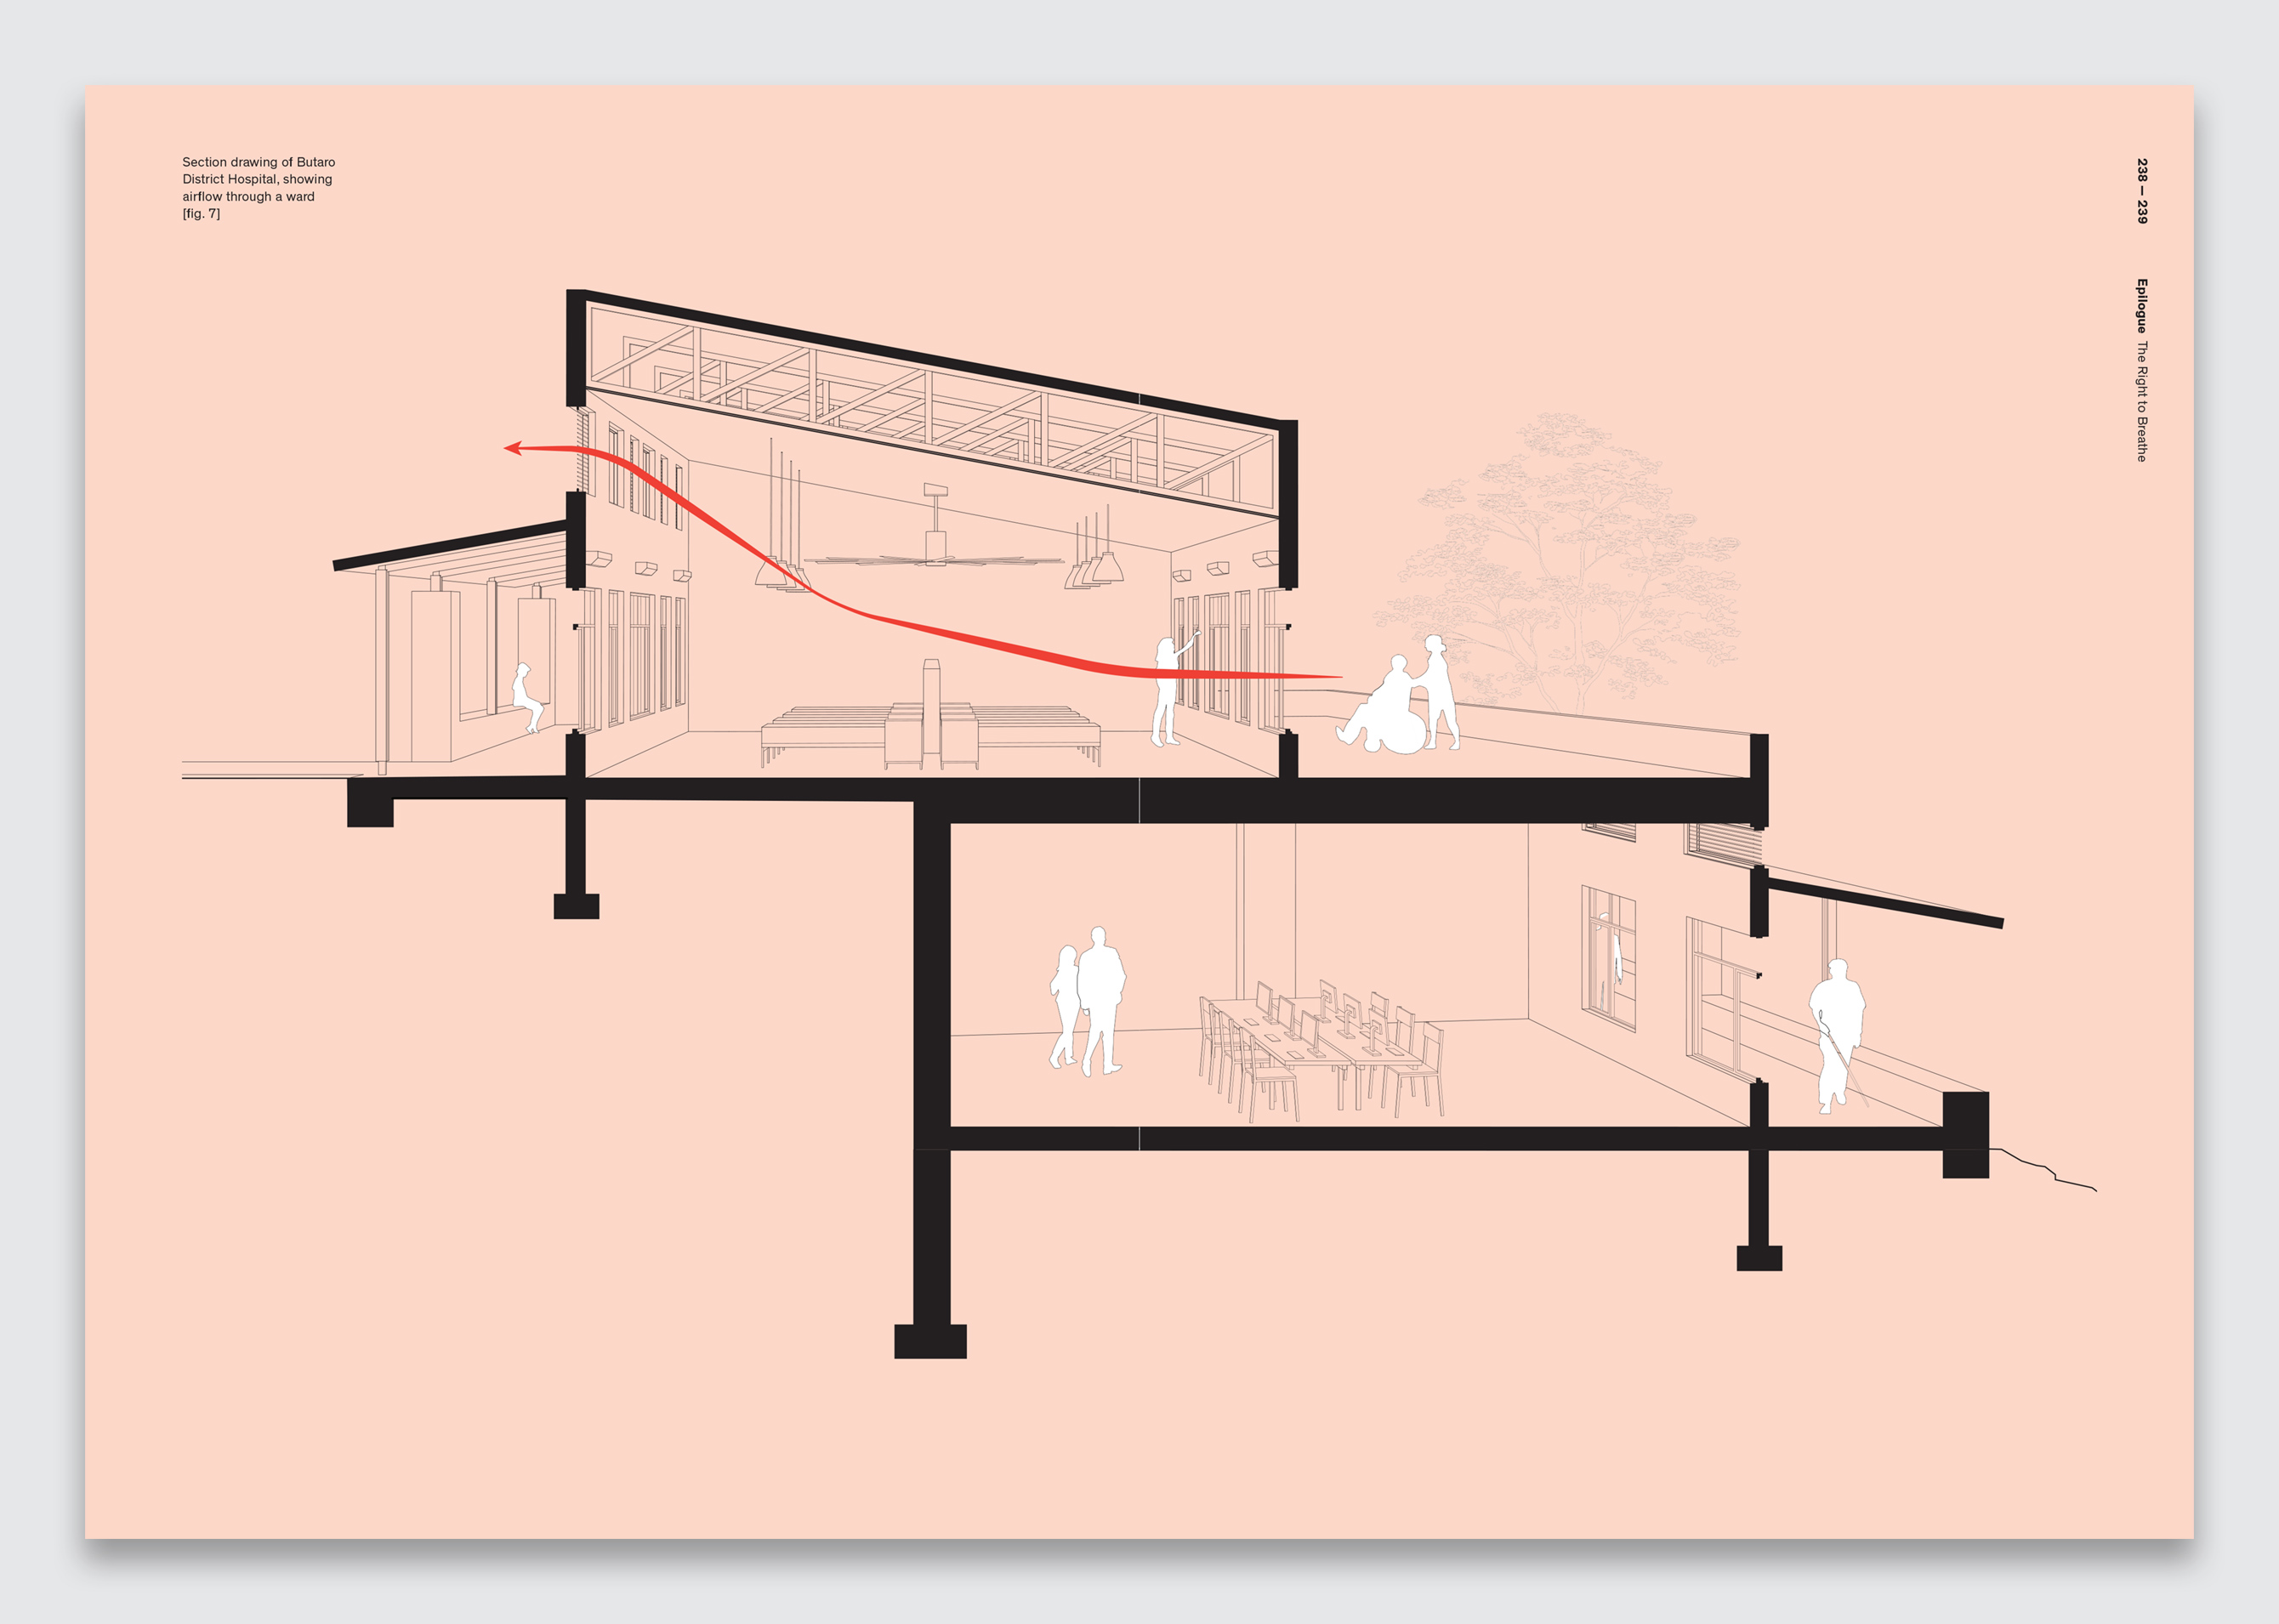
We took Rich at his word, and proposed a medical center with no hallways. In the new construction, all patient, staff members, and public movement and ready usually takes position outdoor. Rwanda’s temperate local weather will allow for at ease exterior waiting through most of the year, but when it rains, protected outside locations supply respite. Exterior hallways necessitated a dispersed multibuilding layout instead than a centrally loaded establishment, and the structures had to be skinny (so air could transfer via them). Doctors would wander amongst properties dispersed in a campus setting, so we created covered pathways surrounded by lush landscaping and gardens to brighten their journey.
Elevators generally split, and in rural areas the upkeep needed is also precise for good upkeep. We wanted a facility that would be accessible without elevators, a single that a patient in a wheelchair could absolutely traverse. Rwanda’s zigzagging hillside footpaths were a useful precedent we layered the healthcare facility across the crests of a hill to make certain that a number of stories would be available at floor amount. This had the supplemental advantage of leaving house for future campus advancement.
The development in both an infection command and affected person encounter was to isolate clients in one rooms. But in rural configurations, Rich informed me, sufferers ended up dying additional generally in isolated rooms since there have been not sufficient team to check them. With out complex checking units, it was needed to have a visible connection in between the nurses’ station and the patient. We made open up wards with nurses’ stations in the middle, lower partitions to make certain the visibility of the total place and all the beds, and couple of corners to block the look at in between employees and client. Glass-doored isolation rooms for actively contagious clients are found at the conclusion of every ward. Adjacent bogs are geared up with their have venting and entrances off the wards to minimize the distribute of odors and bioaerosols.
Nightingale’s structure rules ended up based on
wards that could hold a carefully balanced load of 20 to 30 beds: no considerably less, no far more. In Rwanda, we saw wards made for two dozen individuals holding well more than 30, at times with two to a few men and women for each bed or with individuals lying on mats underneath. With couple of professional medical services in the place, this was easy to understand: medical doctors have been trying to use all the readily available house. But we knew how perilous overcrowding and unregulated scale could be, and we preferred to ensure that the wards in Butaro would not overfill in the course of moments of stress to the procedure.
Nightingale’s prescriptions, I realized, described a parametric marriage between people, spaces, and companies. When a person of these things is out of harmony, the method can split down and clients can get sicker. To concentrate on overcrowding, we amended the Nightingale ward a little, changing the central hallway with a fifty percent-top wall. Patient beds project out from this central wall, dealing with the home windows, and the pathway encircles the ward rather than cutting through the centre of it.
This supplies 3 complementary advantages. 1st, with an immovable wall in the center and smaller sized hallways on the perimeter, team cannot overfill the ward without disrupting the nursing rounds. In this way, we intended towards the draw back of flexibility. Second, this central wall consolidates electrical outlets, connect with buttons, and oxygen sockets, which are positioned in the headboard. Its coloured panels are detachable to permit for the addition of foreseeable future units and for repair service.
The third benefit taught me about the further job of architecture. With their beds oriented to encounter the windows, patients can see the spectacular landscape outdoors. Scholarship has revealed that a straightforward view decreases affected individual keep instances and pain treatment requests. As well as, it was rather evident that it would be preferable to glimpse out a window relatively than gaze at a roomful of other ill men and women. With beds no lengthier arranged along the periphery of the ward, we were being in a position to raise the window dimensions, lowering the sill below headboard peak, and thus deliver much more light-weight, sights, and air into the area. This simple transfer demonstrated that when architectural design is human centered, it can be in harmony with purpose, variety, and knowledge.
“With confined assets,” Farmer once explained to me, “people get resourceful.” This appeared to be the circumstance in Butaro. The new ward style and design, now identified as the Butaro ward, is prepared into countrywide tips, and it has been replicated in hospitals through Rwanda and further than. I am absolutely sure we will see the Butaro ward alter and recalibrate as new services and techniques take about these hospitals. But I was reminded that when physicians struggle for their patients’ accessibility to well being treatment, they are also preventing for their appropriate to breathe clean, uncontaminated air. Nightingale changed a large amount of factors, but most important to us was the revelation that architecture is an essential, rights-primarily based discipline. I realized this on that hill in Rwanda.


